

102 Section I • Excisional Biopsy/Partial Mastectomy
Step 5. Pearls and Pitfalls
1. Pearls
◆ The breast tissue should constantly be felt for consistency throughout the procedure. Biopsy of
suspect areas, despite absence of gamma signals, should be considered.
◆ Hot signals do not defi ne the extent of cancer; ROLL should be regarded only as a localization
aid.
◆ Bilateral nonpalpable breast cancers can be simultaneously localized without any adverse
effects.
◆ ROLL can be combined with sentinel lymph node biopsy (SNOLL).
2. Pitfalls
◆ Check for allergic reactions (i.e., to albumin).
◆ The collimator should be mounted on the tip of the gamma camera. Failure to do so may result
in inability to obtain accurate signals.
◆ Shake the syringe before use. Macroaggregates tend to adhere to the walls of the plastic syringe.
The inadequate mixing of such components could result in inability to obtain signals.
◆ Spillage of injectate along the needle tract should be avoided. The plunger of the syringe is
pushed to the end of the barrel only when the radiologist is certain about the needle tip posi-
tion within the lesion to be injected. Spillage along the needle tract can mislead the surgeon by
giving false-positive signals.
◆ Ensure that the radioisotope is injected into the lesion. In our experience, 1% to 2% of radio-
isotope injections resulted in failed localization. The availability of an alternative method of
localization is recommended in the rare event the radioisotope technique fails.
◆ Small, contained hematomas can be managed conservatively. Large, expanding hematomas may
need open surgical drainage and antibiotics. Allergic reactions to the radioisotope or macroag-
gregates, although possible, have not yet been reported with ROLL.
Chapter 8 • Radioisotope Occult Lesion Localization 103
Bibliography
Audisio RA, Nadeem R, Harris O, et al: Radioguided occult lesion localisation (ROLL) is available in the UK for impalpable breast lesions.
Ann R Coll Surg 2005;87:92-95.
De Cicco C, Pizzamiglio M, Trifi ro G, et al: Radioguided occult lesion localisation (ROLL) and surgical biopsy in breast cancer: Technical
aspects. Q J Nucl Med 2002;46:145-151.
Feggi L, Basaglia E, Corcione S, et al: An original approach in the diagnosis of early breast cancer: Use of the same radiopharmaceutical
for both non-palpable lesions and sentinel node localisation. Eur J Nucl Med 2001;28:1589-1596.
Ferrari M, Cremonesi M, Sacco E, et al: Radiation protection in the use of tracers in radioguided breast surgery. Radiol Med (Torino)
1998;96:607-611.
Gennari R, Galimberti V, De Cicco C, et al: Use of technetium-99m-labeled colloid albumin for preoperative and intraoperative localization
of nonpalpable breast lesions. J Am Coll Surg 200;190:692-698.
Luini A, Zurrida S, Galimberti V, Paganelli G: Radioguided surgery of occult breast lesions. Eur J Cancer 1998;34:204-205.
Luini A, Zurrida S, Paganelli G, et al: Comparison of radioguided excision with wire localization of occult breast lesions. Br J Surg
1999;86:522-525.
Nadeem R, Chagla LS, Harris O, et al: Occult breast lesions: A comparison between radioguided occult lesion localisation (ROLL) vs.
wire-guided lumpectomy (WGL). Breast 2005;14:283-289.
Nadeem R, Chagla LS, Harris O, et al: Tumour localisation with metal coil before the administration of neo-adjuvant chemotherapy. Breast
2005;14:403-407.
Rampaul RS, Dudley NJ, Thompson JZ, et al: Radioisotope for occult lesion localisation (ROLL) of the breast does not require extra radia-
tion protection procedures. Breast 2003;12:150-152.
Ronka R, Krogerus L, Leppanen E, et al: Radio-guided occult lesion localization in patients undergoing breast-conserving surgery and
sentinel node biopsy. Am J Surg 2004;187:491-496.
Thind CR, Desmond S, Harris O, et al: Radio-guided localization of clinically occult breast lesions (ROLL): A DGH experience. Clin Radiol
2005;60:681-686.
Step 1. Surgical Anatomy
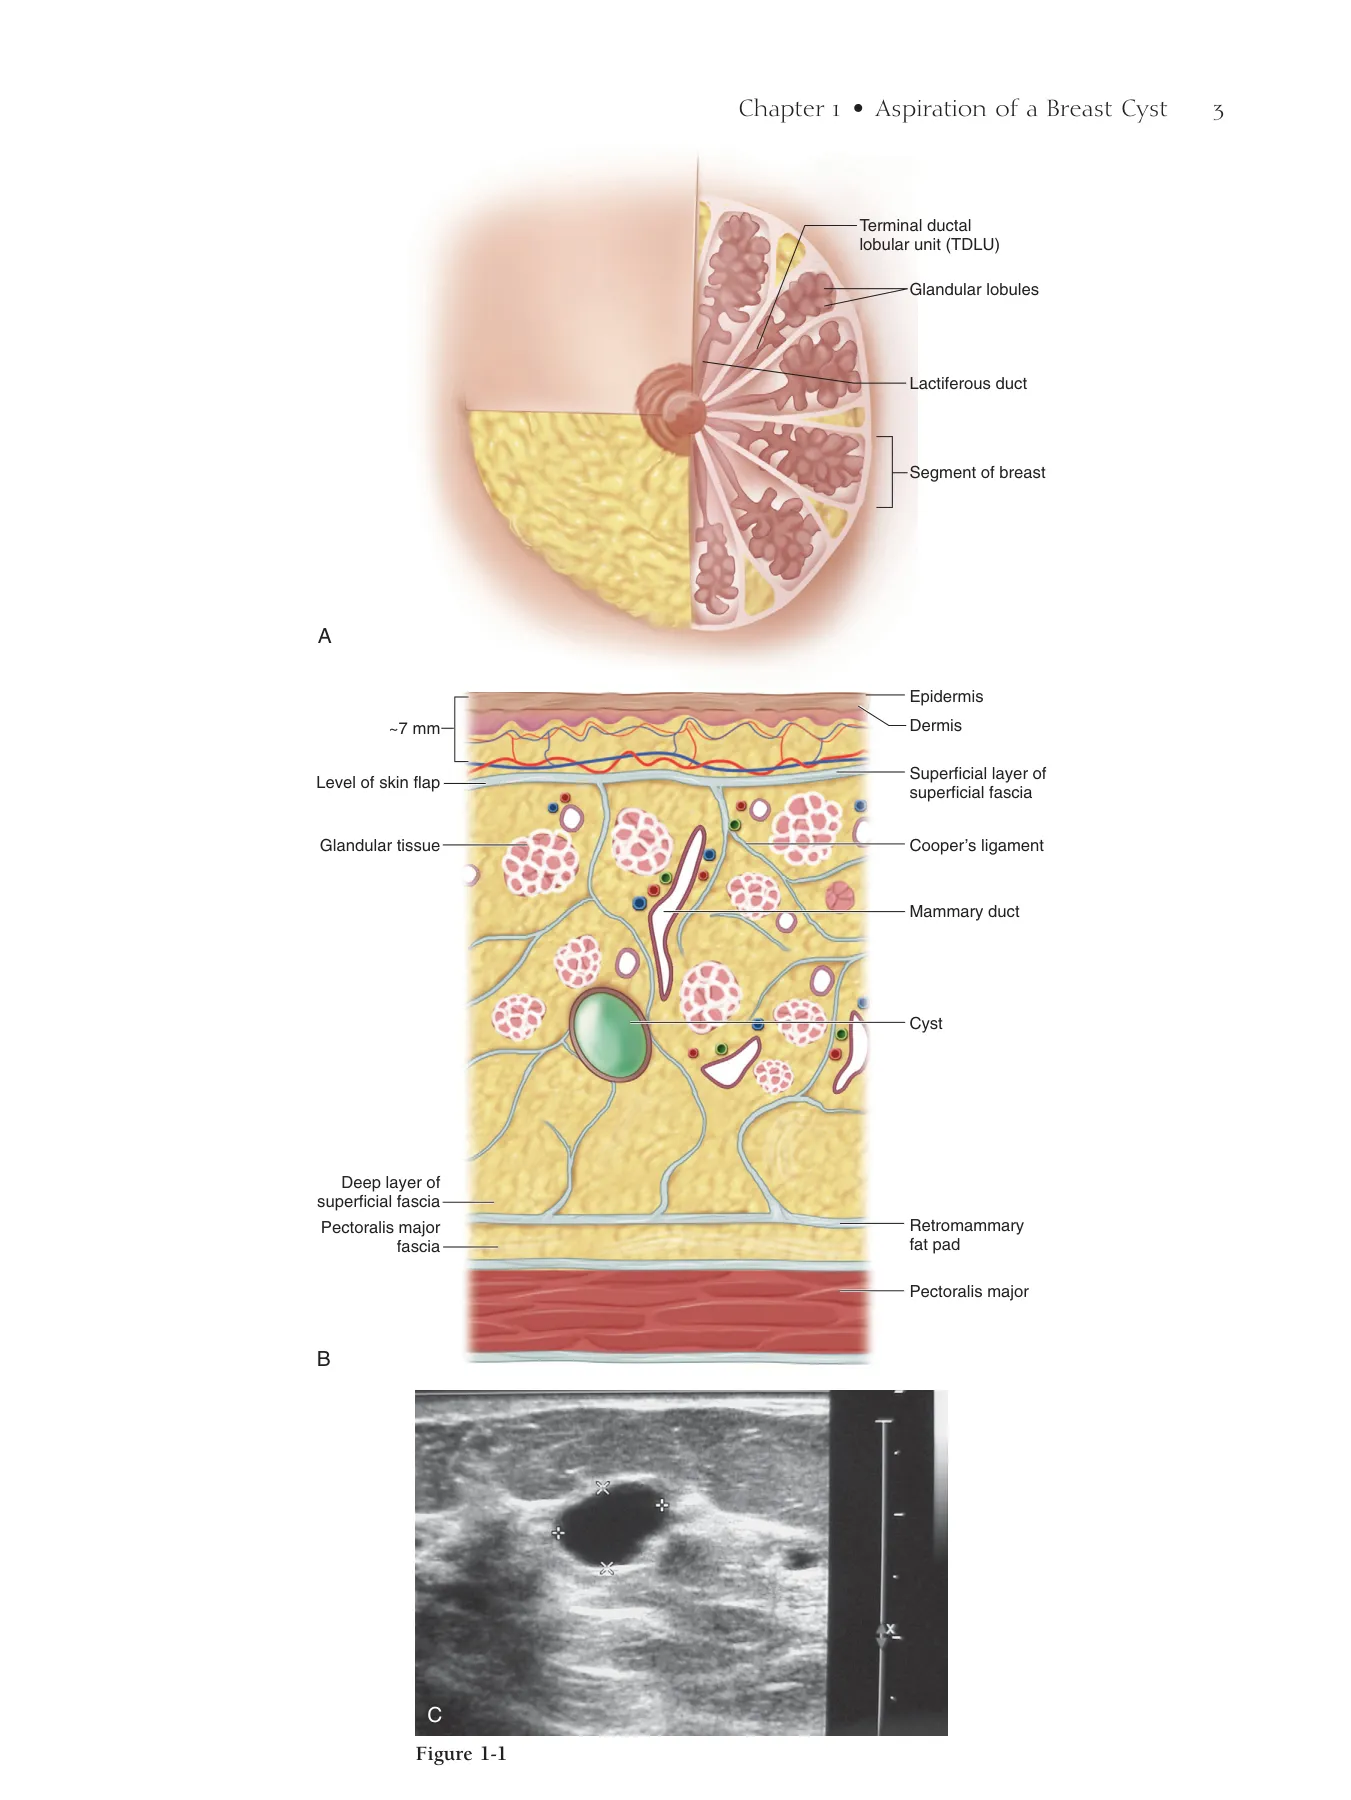
◆ Familiarity with the ultrasonographic characteristics of the normal breast, as well as those of
benign and malignant lesions, is essential.
◆ Figures 9-1 and 9-2 demonstrate the normal anatomy of the breast and its ultrasonographic
appearance.
◆ Figure 9-3 illustrates the more common characteristics that distinguish benign from malignant
lesions.
Step 2. Preoperative Considerations
1. Appropriate Patient Selection
◆ Only patients who have relatively small (<18 mm), unifocal tumors should be offered this
technique. Because the cryoprobe needle has a freezing length of 4 cm, it would be diffi cult to
obtain clear margins in patients with tumors larger than 2 cm.
◆ The lesion must be visible on ultrasonography.
◆ Ideally the mass should be neither very superfi cial nor very deep in the breast.
◆ There are only limited data for the use of this technique in patients with ductal carcinoma in
situ.
◆ The technique should be avoided in patients with invasive lobular carcinomas.
Cryoablation-Assisted
Lumpectomy
Anees B. Chagpar
CHAPTER 9
104
Chapter 9 • Cryoablation-Assisted Lumpectomy 105
Epidermis
Dermis
Superficial layer of
superficial fascia
Cooper’s ligament
Pectoralis major
muscle
Mammary duct
Mass
Retromammary
fat pad
Glandular tissue
Level of skin flap
~7 mm
Pectoralis major
fascia
Deep layer of
superficial fascia
Skin
Subcutaneous
Glandular tissue
Retromammary fat
Pectoral muscle
Pleura
Age - 28
Skin
Subcutaneous
Glandular tissue
Retromammary fat
Pectoral muscle
Pleura
Age - 28
Figure 9-2
Smooth / sharp
Indistinct / jagged
Grows within tissue planes
Disrupted
Transverse > Longitudinal
Longitudinal > Transverse
Posterior enhancement
Posterior shadowing
Benign
Malignant
Margins
Adjacent
architecture
Shape
Retrotumoral
effect
Figure 9-3
Figure 9-1
106 Section I • Excisional Biopsy/Partial Mastectomy
2. Preoperative Diagnostic Core Needle Biopsy for Receptors and Markers
◆ Freezing interferes with immunohistochemical and fl uorescence in situ hybridization tech-
niques for hormone receptor and her-2-neu analysis. Also, tumor grade may be diffi cult to
discern after cryotherapy. Therefore, it is critical to obtain a preoperative core needle biopsy
both for diagnosis and receptor analysis.
3. Equipment Needed
◆ The following equipment is required:
▲ Intraoperative ultrasonography
▲ Cryoprobe needle
▲ Local anesthetic or saline for infi ltration
▲ Usual equipment needed for lumpectomy
Step 3. Operative Steps
1. Anesthesia, Patient Positioning, Draping
◆ This procedure can be done under general anesthesia or conscious sedation with monitored
anesthesia care.
◆ The patient is positioned supine and draped in the usual fashion as is done for a lumpectomy
(Fig. 9-4).
2. Ultrasonography
◆ The mass is visualized using intraoperative ultrasonography in both longitudinal and transverse
axes (Fig. 9-5).
◆ The mass is measured in each axis and the largest measurement of the mass is noted.
Chapter 9 • Cryoablation-Assisted Lumpectomy 107
US of cancer
US of cancer
US of cancer
Figure 9-4
Figure 9-5
108 Section I • Excisional Biopsy/Partial Mastectomy
3. Placement of Probe
◆ While holding the ultrasound probe to visualize the mass in one hand, a small incision is made
with the other hand along the long axis of the transducer.
◆ The cryoprobe needle is inserted toward the mass under ultrasonographic guidance, keeping
the probe parallel to the transducer (Fig. 9-6).
◆ The ultrasonogram demonstrates the longitudinal approach and placement of the cryoprobe
needle in the targeted mass (Fig. 9-7).
◆ Ensure that the probe is placed in the center of the lesion by scanning in the transverse axis.
The probe should be visible as a bright white spot in the middle of the lesion (Fig. 9-8).
Chapter 9 • Cryoablation-Assisted Lumpectomy 109
A
B
Tumor
Needle in
longitudinal view
Tumor
Probe in
transverse view
Figure 9-6
Figure 9-7
Figure 9-8
110 Section I • Excisional Biopsy/Partial Mastectomy
4. Measurements
◆ The probe’s freeze zone has a standard length (usually 4 cm). Therefore, one cannot create a
longer iceball than this, and the shortest axis will be the depth of the iceball, which will change
with the duration of the freezing.
◆ In determining the appropriate depth of the freeze zone, some have considered an 8-mm margin
around the lesion acceptable. Therefore, to determine the depth of freezing required, add the
size of the mass and the extra margin you wish to cover multiplied by two (for the proximal
and distal margins). For example, if the mass is 15 mm and an 8-mm margin is desired, the
total depth of the freeze zone should be 15 mm + (8 mm × 2) = 31 mm (Fig. 9-9).
◆ The mass should be centered in the freeze zone of the probe.
▲ To do this, calculate the distance beyond the edge of the lesion where the tip of the probe
should be placed by subtracting the largest dimension of the lesion from the length of the
freeze zone of the probe, and dividing by two.
▲ The standard freeze length for a probe is 4 cm. If the lesion measures 15 mm, in order to
center the lesion in terms of length one would aim to have (40 − 15)/2 = 12.5 mm of probe
distal to the edge of the mass (see Fig. 9-9).
◆ The probe should be placed in the center of the lesion’s vertical axis.
◆ If the lesion is not perfectly centered, the freeze depth can be modifi ed accordingly. By scanning
in the transverse plane, the longest distance from the probe to the edge of the lesion can be
determined. For example, Figure 9-10 demonstrates a 15-mm lesion in which the probe is
placed too far inferiorly—there is 9 mm from the probe to the top of the lesion. Multiply this
distance by two (as though the probe was in the middle), which gives 18 mm. Given that this
new measurement is greater than the true longest dimension of the lesion (15 mm), the depth
of the iceball should be calculated using the larger measurement: 18 mm + (2 × 8-mm margin)
= 36-mm iceball (see Fig. 9-10).
5. Growth of Iceball
◆ Once the probe is in position and the desired length of the iceball is calculated, the probe is
set to high freeze; argon gas delivered to the probe achieves temperatures of −160° C, thereby
immobilizing the lesion. The freeze process is monitored using real-time ultrasonography until
the iceball reaches the predefi ned length (Fig. 9-11).
◆ Once the iceball reaches this length, the probe is turned to low freeze, which maintains the size
of the iceball. The iceball is maintained at low freeze until it is excised. The freeze may then be
turned off to allow the iceball to slide off the probe.
Chapter 9 • Cryoablation-Assisted Lumpectomy 111
31 mm
12.5 mm
15 mm
40 mm
7.5 mm
36 mm
12.5 mm
15 mm
9 mm
40 mm
Needle
Iceball
Figure 9-9
Figure 9-10
Figure 9-11
112 Section I • Excisional Biopsy/Partial Mastectomy
6. Infi ltration of Local Anesthetic or Saline
◆ As the iceball grows, local anesthetic or saline can be injected to ensure the iceball does not
encroach on the skin or pectoralis muscle (Fig. 9-12).
7. Incision
◆ An incision is made in the usual fashion over the now palpable mass (see Chapter 6 for a com-
plete discussion of excisional breast biopsy).
8. Excision of Iceball
◆ Electrocautery is used to dissect around the palpable mass.
◆ The probe can be used as a lever, allowing the mass to be removed like a lollipop
(Fig. 9-13).
◆ The freeze is turned off and the mass is oriented and removed off the probe.
◆ The probe is removed.
◆ The cavity is irrigated, meticulous hemostasis is achieved, and closure proceeds in the usual
fashion (see Chapter 6).
Step 4. Postoperative Care
◆ Essentially, the postoperative care for patients undergoing cryoablation-assisted lumpectomy is
the same as for patients undergoing a conventional lumpectomy.
◆ Care should be taken to inspect the skin after the procedure because frostbite can be noted.
Chapter 9 • Cryoablation-Assisted Lumpectomy 113
Needle injecting saline
between iceball and skin
Figure 9-12
A
B
Figure 9-13
114 Section I • Excisional Biopsy/Partial Mastectomy
Step 5. Pearls and Pitfalls
1. Preoperative
◆ Appropriate patient selection is critical.
◆ Ensure that an adequate core-needle biopsy has been obtained for preoperative diagnosis and
receptor studies.
2. Intraoperative
◆ Measurements are critical in this procedure. If the probe is eccentrically placed on the transverse
view, this should be taken into consideration when calculating the maximum dimension of the
iceball (see Fig. 9-10).
◆ Infi ltration of local anesthetic to increase the space between the iceball and the skin or pectoralis
muscle not only prevents freezing of the skin or muscle but helps with postoperative pain.
◆ Because the probe freezing can take up to 20 minutes, it is effi cient to start with the
sentinel node biopsy, which is often performed as a concomitant procedure, and perform the
cryoablation-assisted lumpectomy while waiting for the intraoperative evaluation of the sentinel
nodes. The surgeon can close the sentinel node incision while the iceball grows.
◆ The iceball often takes a spherical or elliptical shape that facilitates conformation and place-
ment of a MammoSite (Cytyc Surgical Products, Marlborough, MA) brachytherapy balloon, if
planned.
3. Postoperative
◆ Pathologists may fi nd it more diffi cult to assess tumor grade and hormone receptor status with
the iceball specimen. However, margins are assessed in the usual fashion.
Bibliography
Sabel MS, Kaufman CS, Whitworth P, et al: Cryoablation of early-stage breast cancer: Work-in-progress report of a multi-institutional trial.
Ann Surg Oncol 2004;11:542-549.
Simmons RM: Ablative techniques in the treatment of benign and malignant breast disease. J Am Coll Surg 2003;197:334-338.
Tafra L, Fine R, Whitworth P, et al: Prospective randomized study comparing cryo-assisted and needle-wire localization of ultrasound-visible
breast tumors. Am J Surg 2006;192:462-470.
Tafra L, Smith SJ, Woodward JE, et al: Pilot trial of cryoprobe-assisted breast-conserving surgery for small ultrasound-visible cancers. Ann
Surg Oncol 2003;10:1018-1024.
Step 1. Surgical Anatomy
◆ When performing excision followed by radiofrequency ablation (eRFA), knowledge of the prior
position of the tumor within the lumpectomy cavity and its relationship to the skin and the
chest wall is key to positioning the radiofrequency (RF) probe for appropriate ablation of the
tumor bed margin (Fig. 10-1).
◆ Figure 10-2 illustrates the eRFA concept.
Step 2. Preoperative Considerations
◆ The indications for RFA after lumpectomy for cancer (invasive or noninvasive) include the
following:
▲ To increase margin width without resecting additional tissue
▲ To ablate occult disease in patients who cannot be treated with radiation therapy (e.g., col-
lagen vascular disease, comorbid diseases, prior radiation therapy for conservative breast
cancer treatment), who refuse radiation therapy, or in whom such therapy is of questionable
value.
Step 3. Operative Steps
1. Setup
◆ Excision of breast lesions as well as RFA can be performed under local anesthesia with or
without sedative, or general anesthesia. Local anesthesia using a mixture of short- and long-
acting anesthetics with epinephrine is ideal.
Excision Followed by
Radiofrequency Ablation
V. Suzanne Klimberg
CHAPTER 10
115
116 Section I • Excisional Biopsy/Partial Mastectomy
Terminal ductal
lobular unit (TDLU)
Glandular lobules
Lactiferous duct
Segment of breast
A
Figure 10-1
Lymph node
Milk duct
Lactiferous
duct
Papilloma
Milk gland
Fat
Subcutaneous
abscess
Subareolar
abscess
Cyst
Fascia of
pectoralis major
Retromammary
fat plane
Pectoralis major
Pectoralis minor
Rib
Invasive mammary
carcinoma
B
Ductal carcinoma
in situ (DCIS)
Terminal ductal
lobular unit (TDLU)
Epidermis
Dermis
Superficial layer of
superficial fascia
Cooper’s ligament
Pectoralis major
Mammary duct
Mass
Retromammary
fat pad
Glandular tissue
Level of skin flap
~7 mm
Pectoralis major
fascia
C
Deep layer of
superficial fascia
Undetected
+ margins
Surgical excision
Residual disease
RFA encompasses
new margin
BC
Figure 10-2
Chapter 10 • Excision Followed by Radiofrequency Ablation 117
◆ The patient’s body should be positioned the same as for the immediate prior lumpectomy,
juxtaposed to the edge of the table with the ipsilateral arm at 90 degrees, such that the surgeon
and assistant can stand close to the patient above or below the arm (see Fig. 6-3).
2. Preparation of the Bed for Radiofrequency Ablation
◆ After achieving hemostasis, place a pursestring suture in the cavity at the level of the previous
tumor and bring the cavity together so that the opening is approximately 1 to 2 cm in diameter
(Fig. 10-3).
3. Positioning the Radiofrequency Probe
◆ Deploy the RF probe in the tumor bed so that the tines enter the breast tissue of the lumpec-
tomy bed to a depth of 1 cm (Figs. 10-4 and 10-5).
◆ Place sutures in the skin to pull it away from the area of ablation (Fig. 10-6).
118 Section I • Excisional Biopsy/Partial Mastectomy
Breast
Tumor bed
4 cm
5 cm
RF Probe
Lumpectomy
cavity
Figure 10-3
Figure 10-4
Figure 10-5
Skin retraction sutures
Ablatated cavity with
purse string still in
Figure 10-6
Chapter 10 • Excision Followed by Radiofrequency Ablation 119
4. Ablation
◆ The RF probe is activated to 100° C for 15 minutes.
◆ After the ablation, wait 30 seconds. If the temperature of the probe goes below 55° C, ablate
at 100° C for 5 more minutes.
5. Imaging the Ablation Zone
◆ Use Doppler ultrasonography to determine the width of ablation and to ensure the ablation
zone does not jeopardize the skin. The ablation zone lights up on Doppler secondary to off-
gassing of nitrogen as the tissue is heated (Fig. 10-7). If necessary, retract the RF probe to
protect the skin.
6. Removing the Radiofrequency Probe
◆ Once the ablation is completed, remove the RF probe.
◆ Irrigate the wound to remove debris.
◆ Use electrocautery for hemostasis.
120 Section I • Excisional Biopsy/Partial Mastectomy
A
RF Probe
Doppler
US probe
Skin retracted
B
Skin
Cavity
Doppler of
ablation zone
Figure 10-7
Chapter 10 • Excision Followed by Radiofrequency Ablation 121
7. Confi rming the Margin of Ablation
◆ The surgeon new to eRFA may want to confi rm depth of ablation by using a 6-mm punch
biopsy to at least a 1-cm depth on the superior, inferior, medial, lateral, and posterior margins.
Pathologic study with hematoxylin and eosin stain, proliferating cell nuclear antigen (PCNA),
or a vital stain will confi rm successful ablation.
8. Closure
◆ Only the superfi cial subcutaneous tissue (≥7 mm) is closed (see Fig. 6-11).
◆ Either a running or interrupted absorbable suture can be used to close the dermis. A subcuticu-
lar running stitch is best for closing the skin.
◆ A drain is unnecessary unless good intraoperative hemostasis cannot be achieved.
Step 4. Postoperative Care
◆ A pressure dressing is not necessary. Glue or Steri-Strips oriented horizontally over the wound
is suffi cient.
◆ A sports bra is suffi cient to stabilize the breast for at least the fi rst 48 hours.
122 Section I • Excisional Biopsy/Partial Mastectomy
Step 5. Pearls and Pitfalls
◆ It is necessary only to ablate the area where the tumor was sitting.
◆ When excising a tumor in preparation for eRFA, make the incision directly over the tumor.
◆ Excise the tumor with the intent of obtaining tumor-free margins.
◆ Ensure that the cavity wall is not too thin (≤1 cm) before deploying the RF probe.
◆ Ensure that the skin is kept away from the probe so that steam from the ablation does not burn
the skin.
◆ A step ablation (overlapping a deep with a more superfi cial ablation) can be performed if the
tumor bed span is greater than the depth of a single ablation.
Bibliography
Bland KL, Gass J, Klimberg VS: Radiofrequency, cryoablation, and other modalities for breast cancer ablation. Surg Clin North Am
2007;87:539-550.
Klimberg VS, Kepple J, Shafi rstein G, et al: eRFA: Excision followed by RFA—a new technique to improve local control in breast cancer.
Ann Surg Oncol 2006;13:1422-1433.
Step 1. Surgical Anatomy
◆ Figure 11-1 shows the anatomic structures that must be considered with an axillary sentinel
lymph node biopsy (SLNB).
Step 2. Preoperative Considerations
◆ The indications for SLNB include the following:
▲ Use SLNB for patients with lesions clinically less than stage T2, clinically negative nodes,
and no metastases.
▲ Consider using SLNB in stage T3 lesions, locally advanced tumors, or multicentric cancers,
but there are few data and such patients should be enrolled in available clinical trials.
▲ The concordance of SLN with axillary lymph node dissection (ALND) results is much less
for patients with signifi cant disturbance of the breast, such as previous axillary surgery, pre-
operative radiation or chemotherapy, or large upper outer quadrant excisions (ones that
would block major lymphatics to the axilla). Use SLNB cautiously in such patients.
▲ Consider using SLNB alone for aggressive (ductal carcinoma in situ [DCIS]) or large (>2.5 cm)
lesions instead of a level I dissection.
Axillary Sentinel Lymph
Node Biopsy
V. Suzanne Klimberg
CHAPTER 11
124
Chapter 11 • Axillary Sentinel Lymph Node Biopsy 125
Breast cancer
Nipple/areola
SLN
ARM
Rib
Intermammary
chain
Figure 11-1
126 Section II • Lymph Node Biopsy
Step 3. Operative Steps
1. Setup
◆ Available materials for the localization and biopsy of the SLN include blue dye (1% isosulfan
blue [Lymphazurin], dilute methylene blue, and vital blue dye) and technetium-99m (99mTc)
sulfur colloid (fi ltered or unfi ltered) or 99mTc albumin. The materials may be used alone or in
combination.
◆ The timing and location of the injection can be varied until you fi nd the technique that works
well for you and your institution’s facilities. Avoid local anesthesia because it may disturb the
migration properties of the tracers. If the injection is given before general anesthesia, the patient
should assume the supine position to avoid injury from a fainting episode.
2. Injection of Radiocolloid
◆ The surgeon or the radiologist can inject the 99mTc tracer in the nuclear medicine suite or other
radiation safety-approved areas (Fig. 11-2).
◆ The tracer can be injected intraoperatively or up to 24 hours before surgery, with similar good
results.
◆ Injection methods include peritumoral, within about 1 cm of the tumor (such intraparenchymal
injections can be guided by palpation or ultrasonography); intratumoral; dermal (intradermal
or subdermal); subareolar; and combinations thereof (Fig. 11-3).
◆ Radiotracer is the only way to locate the SLN before incision, and can identify SLNs located
outside the axilla (8% of cases; e.g., internal mammary, supraclavicular, thyroid).
◆ Radiation exposure is minimal even for the busy surgeon and far less for other staff.
Chapter 11 • Axillary Sentinel Lymph Node Biopsy 127
Figure 11-2
Intratumoral injection
Dermal injection
Peritumoral injection
Subareolar injection
Subareolar
plexus
Limbus
A
B
D
C
Figure 11-3
128 Section II • Lymph Node Biopsy
3. Injection of Blue Dye
◆ Injection methods for the blue dye are similar to those for the radiotracer. Inject the dye
approximately 5 minutes before the procedure for outer quadrant lesions using subareolar,
peritumoral, or intratumoral placement, or dermally when there is an upper outer scar (Fig.
11-4). Inject 10 to 15 minutes before the procedure if injecting intra parenchymally for inner
quadrant tumors.
◆ If 20 minutes or more has elapsed since the injection of blue dye and the biopsy procedure has
not yet begun, consider injecting another dose.
◆ Inform the anesthesiologist when the blue dye is injected because it may cause a decrease in
the patient’s oxygen saturation. Likewise, recovery room personnel and family members should
be notifi ed about blue dye injection because the oxygen saturation will continue to be low and
the patient will appear ashen.
◆ Life-threatening allergic reactions, some delayed for several hours, have been reported with the
injection of blue dye. The anesthesiologist should be alert for a rise in peak airway pressures,
and the surgeon for the appearance of a blue rash (Fig. 11-5). Most allergic reactions can be
avoided by not using blue dye in patients with allergies to cosmetics that contain blue dyes.
4. Mapping a Zone of Diffusion
◆ Map out a zone of diffusion using the hand-held gamma probe. Adjust the gamma probe’s
sensitivity so the zone of diffusion does not overlap with any lymph node basins.
◆ If the zone of diffusion overlaps any of the lymph node–bearing areas, the location of the true
SLN may be obscured. In the largest multicenter trial, all false-negative SLNs were from peri-
tumoral injections in the upper outer quadrant, presumably because the zone of diffusion
overlapped the true SLN (Fig. 11-6).
◆ Avoid overlap by decreasing the sensitivity of the gamma probe or use a collimator on the
gamma probe to decrease the infl uence of scatter.
5. Preincision Localization of Sentinel Lymph Node
◆ Check for radiotracer migration to and location of the SLN by preoperative lymphoscintigraphy,
bearing in mind this technique’s low sensitivity (Fig. 11-7).
◆ A hand-held gamma probe is very sensitive for intraoperative location of the SLN. Some studies
indicate that approximately 8% of SLNs are located outside the axilla proper (level II and III,
internal mammary, supraclavicular, thyroid, pectoralis, intramammary, upper abdomen).
◆ Scan and mark any “hot spots” before incision.
◆ If the SLN cannot be localized before incision, inject approximately 40 mL of injectable saline
in the same manner in which the 99mTc was injected. Massage 5 minutes and try again. If there
still is no localization, proceed with skin incision in the axilla.
Chapter 11 • Axillary Sentinel Lymph Node Biopsy 129
Craniad
Tumor
Zone of
diffusion
SLN “Hot spot”
Caudad
Axillary SLN
Zone of
Diffusion
Axillary SLN
Zone of
Diffusion
Figure 11-4
Figure 11-5
Figure 11-6
Figure 11-7
130 Section II • Lymph Node Biopsy
6. Background Count
◆ Once a potential SLN has been located, take a background count 1 to 2 cm away from the hot
spot. A ratio of hot spot-to-background counts of 10 to 1 establishes SLN localization.
7. Skin Incision
◆ Make a 2- to 3-cm incision directly over the hot spot, wherever it is located. If no radiotracer
has been used or it has failed to localize the SLN, make the skin incision just below the hairline
in the anterior axillary line, posterior and perpendicular to the pectoralis major (PM; Fig.
11-8).
◆ Use either cautery or blunt dissection through the subcutaneous tissue (Fig. 11-9, A) down to
the axillary fascia (Fig. 11-9, B), with retractors to provide exposure.
8. Incision of Axillary Fascia
◆ Incise both layers of axillary fascia parallel to the plane of the incision. Disregard any blue
dye above the fascia because all the axillary lymph nodes are located under the fascia.
Chapter 11 • Axillary Sentinel Lymph Node Biopsy 131
PM border
Left hair-
bearing area
Lattisimus border
PM border
Left hair-
bearing area
Lattisimus border
Figure 11-8
A
Fascia
Fascia
B
Figure 11-9
132 Section II • Lymph Node Biopsy
9. Line-of-Sight Dissection
◆ With dual injection of blue dye and radiotracer, the SLN may be “hot” (radioactive), blue, both,
or only palpable. All are indications of sentinel status, so such nodes should be harvested. The
gamma probe is inserted into the wound and slowly rocked back and forth in all directions to
fi nd the “hottest” (i.e., increased counts) direction in which to proceed. As you dissect through
the fatty plane of the axilla, keep bringing the gamma probe (GP) in and out of the wound,
constantly checking direction (“line of sight”; Fig. 11-10).
◆ As the dissection proceeds down toward the SLN, the counts should get higher. If you dissect
away from the SLN, the counts will decrease. Make sure you have not dissected past the SLN
or retracted the SLN after repositioning of instruments. If you still cannot fi nd the SLN, remove
all retractors and start over from the skin down.
10. Excision of Sentinel Lymph Node(s)
◆ Once the axillary fascia is incised, care should be taken not to disturb any blue lymphatics
(Fig. 11-11). Blue lymphatics should be followed to their destination, using the GP as well if
radiotracer was injected. Dissect down to but do not lift up the SLN to avoid misidentifi cation
of the SLN.
◆ Avoid skeletonizing the SLN. Metastases are not uncommonly found in the vessel leading to
the fat around the SLN. Gently dissect parallel to the plane of the lymphatic, following it to a
blue SLN, and use a noncrushing Allis clamp to secure the SLN (Fig. 11-12).
◆ Once either a hot and/or blue node is found, it may be excised using the surgeon’s preferred
technique, as long as care is taken to tie, clip, or cauterize the leading lymphatic vessel.
◆ Unligated lymphatics may lead to a lymphocele (lymph collection) in the lymph node dissection
bed.
Chapter 11 • Axillary Sentinel Lymph Node Biopsy 133
Caudad
Craniad
Right arm
GP
A
GP
B
SLN
Blue lymphatic
leading to blue node
Blue lymphatic
leading to blue node
Babcock on blue node
Babcock on blue node
Figure 11-10
Figure 11-11
Figure 11-12
134 Section II • Lymph Node Biopsy
11. Ex Vivo Count
◆ Take counts on all lymph nodes removed.
◆ Direct the GP up and away from the patient and press the SLN onto the tip of the probe
(Fig. 11-13).
12. Palpation of Axillary Bed
◆ Palpate the bed of dissection to locate any suspect palpable lymph nodes. Theoretically, lymph
nodes blocked by tumor could divert the tracer to an alternate lymph node.
13. Bed Count
◆ Take a fi nal bed count after all SLNs have been removed. If the bed count is higher than 10%
of the background count, make a thorough search for additional SLNs. If there is suffi cient
overlap with the zone of diffusion, it may be impossible to obtain a bed count lower than 10%
of the SLN count.
14. Pathology
◆ Intraoperative techniques for evaluation of the SLN include touch preparation or imprint
cytology and frozen section.
Chapter 11 • Axillary Sentinel Lymph Node Biopsy 135
Figure 11-13
136 Section II • Lymph Node Biopsy
15. Intraoperative Assessment of Sentinel Lymph Node
◆ If it is available, use touch preparation cytology, which involves “stamping” the cut SLN pieces
(3-mm cuts for SLNs > 5 mm) onto a glass slide and performing a hematoxylin and eosin (H&E)
stain.
◆ Use frozen section cautiously on one or multiple pieces of the SLN.
◆ Touch preparation is faster and in general equally as or more accurate than frozen section, and
does not run the risk of missing a diagnosis of micrometastasis.
◆ The College of American Pathologists does not recommend the use of special cytokeratin stains,
except when suspicion is raised but not confi rmed by fi nal H&E staining.
16. Hemostasis
◆ Achieve hemostasis with clip, tie, or electrocautery, but take care when deep in the axilla to
avoid the thoracodorsal or long thoracic nerve. Use nonparalyzing anesthesia to aid in recogniz-
ing impending nerve injury.
17. Closure
◆ Close the axillary or other fascia in layers with 3-0 absorbable sutures (Fig. 11-14). Lack of
closure of the axillary fascia encourages formation of a lymphocele. However, there is no need
for a drain.
18. Dressing
◆ Steri-Strips parallel to the incision or wound glue are suffi cient. Such a dressing allows the
patient to shower immediately after surgery. There is no need for a drain or pressure
dressing.
Chapter 11 • Axillary Sentinel Lymph Node Biopsy 137
Fascial edge
Figure 11-14
138 Section II • Lymph Node Biopsy
Step 4. Postoperative Care
◆ Caution the patient against signifi cant arm movement or any exercise that would jostle the
breast and axilla.
◆ As soon as the wound is healed (average, <1 week), mobilize the patient’s arm to regain range
of motion. Frozen shoulder occurs with SLNB in less than 1% of patients and is usually associ-
ated with reconstruction or mastectomy, in which the patient has been immobilized for longer
periods. Avoid this risk by starting the patient on range-of-motion exercises on the fi rst post-
operative visit. Consult occupational therapy if the arm is not fully mobile at 1 month.
Step 5. Pearls and Pitfalls
◆ If a blue dye reaction is suspected, give the patient 50 mg diphenhydramine intravenously. If
there is no doubt, add 100 mg of methylprednisolone. Admit the patient for close observation
for at least 24 hours.
◆ If oxygen desaturation occurs, do nothing if there are no other indications of a problem and
the desaturation coincides with blue dye injection. This is a false desaturation and is simply a
monitoring problem.
◆ If a blue or hot SLN cannot be identifi ed in a patient with invasive cancer, the axilla must be
staged with an axillary lymph node dissection. In a patient with DCIS without known invasive
cancer, do nothing further. If the patient has a very aggressive DCIS, consider performing a
level I axillary lymph node dissection (simple extended mastectomy; see Chapter 16).
◆ Perform an axillary lymph node dissection when you cannot localize an SLN in the axilla, even
if one was located outside the axilla.
◆ Postsurgical hemorrhage can occur immediately and up to 10 days after surgery. Hemolysis of
clots in the wound can occur during this time and bleeding may be exacerbated by exercise.
Only immediate, large postoperative hematomas need reexploration. Smaller hematomas should
be followed and, if progressing, should be reexplored.
◆ Sensory defi cit of some type can occur early on (fi rst few weeks) and resolves on its own. Reas-
sure the patient. Observe any motor defi cit of the long thoracic or thoracodorsal nerve for up
to 6 weeks because such a presentation most likely represents a neuropraxia rather than a
severed nerve. If the defi cit persists after 6 weeks, reexplore the wound for potential
reanastomosis.
Chapter 11 • Axillary Sentinel Lymph Node Biopsy 139
◆ If nerve damage is recognized during surgery, repair with 6.0 absorbable suture.
◆ For a frozen shoulder, consult occupational or physical therapy for range-of-motion exercises.
Water aerobics are also helpful.
◆ If a lymphocele develops, use a 20-gauge syringe to aspirate it, similar to the procedure used
for a simple cyst aspiration. See the patient every 3 to 4 days until the lymphocele is
resolved.
◆ On intraoperative pathology, a false-positive result is rare, but a false-negative is not. Therefore,
rely on the fi nal formalin-fi xed results for treatment.
◆ Treat the patient based on the results of the fi nal H&E stain. If intraoperative pathology gave
a false-negative reading of the SLN and the SLN turns out to be positive, take the patient back
to the operating room for an axillary lymph node dissection, or arrange for randomization on
an available clinical trial.
Bibliography
American Society of Breast Surgeons: Statement on Sentinel Lymph Node Biopsy. Available at:
Harlow SP, Krag DN: Sentinel lymph node—why study it: Implications of the B-32 study. Semin Surg Oncol 2001;20:224-229.
Grube BJ, Giuliano AE: Observation of the breast cancer patient with a tumor-positive sentinel node: Implications of the ACOSOG Z0011
trial. Semin Surg Oncol 2001;20:230-237.
Orr RK: The impact of prophylactic axillary node dissection on breast cancer survival: A bayesian meta-analysis. Ann Surg Oncol
1999;6:109-116.
Schwartz GF, Giuliano AE, Veronesi U: Proceeding of the consensus conference of the role of sentinel lymph node biopsy in carcinoma
or the breast April 19-22, 2001, Philadelphia, PA, USA. Breast J 2002;8:124-138.
Tuttle TM, Zogakis TG, Dunst CM, et al: A review of technical aspects of sentinel lymph node identifi cation for breast cancer. J Am Coll
Surg 2002;195:261-268.
Step 1. Surgical Anatomy
◆ The internal mammary (IM) lymph node chain is confi ned in the anterior extrapleural chest
space, leaning on the so-called transverse thoracic muscle, which is often involuted to a thin
aponeurotic fascia. The fusion between the visceral and parietal pleura usually begins 2.5 to
3 cm from the lateral sternal border (Fig. 12-1).
◆ The internal mammary artery (IMA) runs through this space along the lateral sternal border,
with its distance from the border increasing from 10 mm at the fi rst intercostal space to 20 mm
at the sixth space.
◆ At the third intercostal space, the IMA is usually 12 to 13 mm from the sternal border.
◆ From the IMA originate the anterior intercostal arteries, two for each intercostal space, running
between the two intercostal muscles, one inferior and the other superior, both anastomosed
with the posterior intercostal artery (see Fig. 12-1). Other minor collateral veins go to the
transverse thoracic muscle.
◆ The IM lymph nodes are usually located in the same plane as the IM vessels or in an anterior
plane, within the fatty tissue surrounding the artery and veins. There are usually four to six
nodes per site, with different distribution in the intercostal spaces (Fig. 12-2).
◆ Usually there is one node in each intercostal space. In the fi rst and second spaces, the lymph
node is usually medial to the IM vessels, whereas in the inferior spaces they are lateral to the
vessels (see Fig. 12-2). Usually no lymph nodes are found below the heads of the ribs.
◆ Two IM veins run along the artery, one medially and the other laterally. The medial vein is
usually the smaller of the two (see Fig. 12-1). These two veins have collaterals similar to those
of the IMA.
◆ The lymphatic vessels of the medial portion of the breast, and especially those located in the
deep portion of the breast, lead to the IM chain. These lymphatics cross the major pectoral
muscle in its medial aspect and traverse the subsequent intercostal muscles. A small number
of nodes are occasionally found in the thin lymphatic net located between the external and the
internal intercostal muscles. The lymphatics that cross the internal intercostal muscle go to the
IM nodes.
Mediastinal Sentinel
Lymph Node Biopsy
Virgilio Sacchini and Alice Chung
CHAPTER 12
140
Chapter 12 • Mediastinal Sentinel Lymph Node Biopsy 141
Sternum (under muscle)
Pectoralis major
muscle (turned back)
Internal mammary
node
Internal mammary
node
Chondrosternal
joint
Second rib
Intercostal
nerve
Internal intercostal
muscle
Pectoralis
fascia
Lung below
parietal pleura
Intercostal
vessels
Internal
mammary artery
Internal
mammary vein
Figure 12-1
Internal Mammary Chain
A
B
Internal
mammary
artery
Costo-sternal
fascia
Transversus
thoracis
muscle
Fat
Pleura
Lymph node
Intercostal
muscles
Anterior
intercostal
membrane
Costal cartilage
Costal cartilage
Pectoralis major
muscle and fascia
Internal mammary
artery
Internal mammary
vein
Internal mammary
nodes along internal
mammary chain
Figure 12-2
142 Section II • Lymph Node Biopsy
1. Indications for Procedure
◆ Complete removal of the IM chain en bloc with the parietal pleura, transected IM vessels, rib,
and intercostal muscle, as well as the major pectoral muscle and the breast, has been described
extensively by several authors. These authors completed subset studies or clinical trials compar-
ing the standard Halsted mastectomy with this extended procedure. In all cases, the authors
reported no benefi t in survival and an increased morbidity and mortality with the extended
procedure.
◆ The introduction of the sentinel node technique in breast cancer has led to the detection of
sentinel nodes outside of the axilla.
◆ Some believe that mediastinal sentinel lymph node biopsy (MSLNB) leads to more accurate
staging and contributes to the overall management of the patient with breast cancer.
◆ MSLNB is a feasible, low-risk operation when directed by radio-guided lymph node
mapping.
◆ Maximally accurate staging should improve the “individualization” of treatment, contributing
to reduced incidence of overtreatment or undertreatment. The American Joint Committee on
Cancer has included the status of the IM lymph node biopsy in defi ning the stage of breast
cancer.
◆ Differences in survival according to degree of axillary or IM involvement were well reported in
studies with long-term follow-up of extended radical mastectomies.
◆ Migration of the staging based on information obtained from IM biopsy has been reported in
10% of cases.
◆ Others claim that migration of the stage may not dramatically infl uence the choice of adjuvant
therapy.
◆ MSLNB should be considered:
▲ When the node is visible on lymphoscintigraphy.
▲ When a positive IM node may change the systemic treatment, in particular when the change
is from a hormonal adjuvant treatment to chemotherapy (e.g., negative axillary sentinel node
biopsy, small cancers, hormonal receptor positive).
◆ Patients with enlarged mediastinal or IM lymph nodes demonstrated on preoperative computed
tomography or magnetic resonance imaging scans may also be considered appropriate candi-
dates for this operation.
◆ Because the overall survival benefi ts of IM lymph node biopsy remain unconfi rmed, the tech-
nique of IM sentinel node biopsy should be as nonaggressive as possible to minimize potential
complications or cosmetic sequelae.
Step 2. Preoperative Considerations
◆ Preoperative lymphoscintigraphy with peritumoral injection of radioisotope is performed
(Fig. 12-3). This will guide the dissection to the appropriate interspace. Lymphazurin blue dye
may be injected intradermally or intraparenchymally before the start of the procedure. However,
the value of blue dye mapping in IM node biopsy is limited. The superfi cial lymphatics that
take up the blue dye will not likely drain to the deep IM nodes, and use of a peritumoral injec-
tion will require blind dissection of the IM basin without knowing to which interspace the dis-
section should be directed.
◆ The normal rate of identifi cation of IM lymph nodes as sentinel nodes ranges between 0% and
4%, with some authors reporting 60% when the isotope injection was performed deeply in the
breast, close to the fascia of the pectoralis major.
Chapter 12 • Mediastinal Sentinel Lymph Node Biopsy 143
Right oblique anterior
Anterior
A
B
Localization of isotope
to the axilla
Site of isotope
injection
Localization
of isotope
to the axilla
Localization
of isotope
to the IM node
Site of
isotope
injection
Figure 12-3
144 Section II • Lymph Node Biopsy
Step 3. Operative Steps
1. Incision
◆ This procedure is usually performed under general anesthesia, although there have been reports
of cases performed under local anesthesia with sedation. Therefore, preoperative assessment for
patients undergoing IM node biopsy is no different than for any patient undergoing standard
axillary sentinel node biopsy with possible axillary lymph node dissection.
◆ Access to the IM node is usually obtained through a wide excision or mastectomy incision.
Only occasionally is a new skin incision required. In these cases, we recommended a 3-cm
curvilinear incision 3 to 4 cm from the lateral sternal margin, for cosmetic purposes
(Fig. 12-4).
◆ The pectoral major muscle is exposed for 2 to 3 cm linearly from the nipple to the lateral sternal
border. In the case of breast conservation surgery, the breast parenchyma should be detached
from the major pectoral fascia to achieve this exposure (Fig. 12-5).
Chapter 12 • Mediastinal Sentinel Lymph Node Biopsy 145
A
B
C
Figure 12-4
Figure 12-5
146 Section II • Lymph Node Biopsy
◆ The muscle is then split to expose the superior intercostal space (Fig. 12-6). Some vessels may
run along the fi bers of the pectoralis major, requiring coagulation or ligation.
◆ The external and internal intercostal muscles are cut transversely from the sternal border in a
lateral direction for 3 to 4 cm (Fig. 12-7). The division should be done in the middle, between
the two ribs or along the superior costal border, to avoid injury of the anterior intercostal vessels.
In cutting the internal intercostal muscle, particular care must be taken to avoid injury to the
inferior parietal pleura.
Chapter 12 • Mediastinal Sentinel Lymph Node Biopsy 147
Intercostal space
Pectoralis muscle
fibers (split)
Rib
A
B
Rib
Figure 12-6
Intercostal space
(intercostal muscles
divided)
Intermammary
node
Intermammary
vessels
Pectoralis muscle
(split)
Rib
A
B
C
Intercostals retracted
IM vessels
Figure 12-7
148 Section II • Lymph Node Biopsy
◆ The IM vessels are surrounded by adipose and lymphatic tissue. They are situated in an extra-
pleural space starting 2.5 to 3 cm from the medial border of the lung (see Fig. 12-7). Confi ning
the dissection to this space helps to prevent injury of the pleura. The artery and veins are usually
covered by fi brous fatty tissue, which is separated, and the small vessels are coagulated. The
artery is usually found 10 to 15 mm from the lateral sternal border.
◆ Figure 12-8 shows the MSLN at the angle of the intercostal vessels and the IM vessels.
◆ A vessel loop is placed to encircle the IM artery (Fig. 12-10). This prevents major bleeding in
the case of inadvertent injury. The vessel loop may also prevent retraction of the artery in case
of transection. If transection does occur, prompt disarticulation or transection of the rib should
be done to clamp the open artery. The largest IM vein, usually lateral to the artery, may also
be encircled. During this maneuver, some small venous collaterals may bleed, requiring coagu-
lation or ligature. If bleeding occurs, the vein may be ligated or clipped. Particular attention
should be paid to preserving the IMA because it is a major resource in the event of coronary
reperfusion surgery.
◆ The perivasal adipose tissue is then divided with the scissors, and the gamma probe is used to
locate the node. In the case of a hot node, the probe indicates its precise position. The node
may be medial or lateral to the vessels. Once identifi ed, the node should be handled with care
to avoid coagulation or disruption of the capsule, where micrometastases are most frequently
found. Small vessels around the node may be coagulated or clipped (Fig. 12-9).
Chapter 12 • Mediastinal Sentinel Lymph Node Biopsy 149
A
IMLN
Intercostal
retracted
Rib
IM vessels
B
IMLN
Figure 12-8
Dissection of internal
mammary node
Vessel loop
surrounding internal
mammary vein
Vessel loop
surrounding internal
mammary artery
Figure 12-9
Figure 12-10
150 Section II • Lymph Node Biopsy
2. Closing
◆ Once the node is removed, the surgical fi eld may be irrigated and examined for abnormal
bubbles to confi rm the integrity of the pleura (Fig. 12-11, A), and the split intercostal and
pectoral muscle is then sutured using 2-0 polyglactin, avoiding excessive traction that may
transect the muscular fi bers (Fig. 12-11, B). The breast parenchyma may be reapproximated
to restore the shape of the breast in case of conservative surgery, and the skin closed
(Fig. 12-12).
Step 4. Postoperative Care
◆ The average time of the procedure is 18 minutes; there is no additional postoperative care
required.
◆ Routine chest radiography is not required unless a pneumothorax is suspected.
◆ In the event of a pneumothorax, a chest tube is not necessary unless the lung itself has been
injured.
◆ Postoperative antibiotics are not indicated unless required for other conditions.
Chapter 12 • Mediastinal Sentinel Lymph Node Biopsy 151
Figure 12-12
A
IM vessels
B
Figure 12-11
152 Section II • Lymph Node Biopsy
Step 5. Pearls and Pitfalls
◆ Preoperative lymphoscintigraphy is the essential tool in the preoperative and intraoperative
planning of IM node biopsy. In the equivocal case, intraoperative ultrasonography may be used
to identify whether an IM lymph node is of suffi cient size to warrant dissection.
◆ During division of the intercostal muscles to gain access to the IM nodes, the interspace may
be very narrow. In this case, removal of the panel of intercostal muscles between the appropri-
ate ribs may provide better exposure.
◆ Injury to the underlying pleura may occur during division of the internal intercostal muscle.
If an injury is recognized intraoperatively, it can easily be repaired with fi ne absorbable
suture.
◆ The placement of vessel loops around the IM vessels aids in preventing major bleeding in the
case of iatrogenic injury to the artery or vein. The vessel loop can prevent retraction of the
vessel in the case of arterial or venous transection and allow for prompt repair or ligation. In
such a case, disarticulation or transection of the rib should be performed to allow control of
the artery. Care must be taken to preserve the IMA as it may become necessary as a conduit
for coronary reperfusion or pedicled transverse rectus abdominis muscle reconstruction.
◆ If an injury involves pneumothorax, the pleura may be sutured with 3-0 polyglactin. A red
rubber catheter is used to evacuate air from the pleural space.
◆ Special consideration should be given to patients who have had previous median sternotomy
with bypass using the IMA as a conduit to the coronary vessels. The plane of the IM nodes
has been disturbed by prior dissection of the IMA and the procedure carries more risk in
this case.
◆ Patients with breast implants may also pose a challenge in gaining adequate exposure of the IM
nodes. IM node biopsy is still feasible in these patients, but dissection of the implant away from
the biopsy fi eld should be performed outside of the capsule, with care taken to avoid punctur-
ing the implant.